


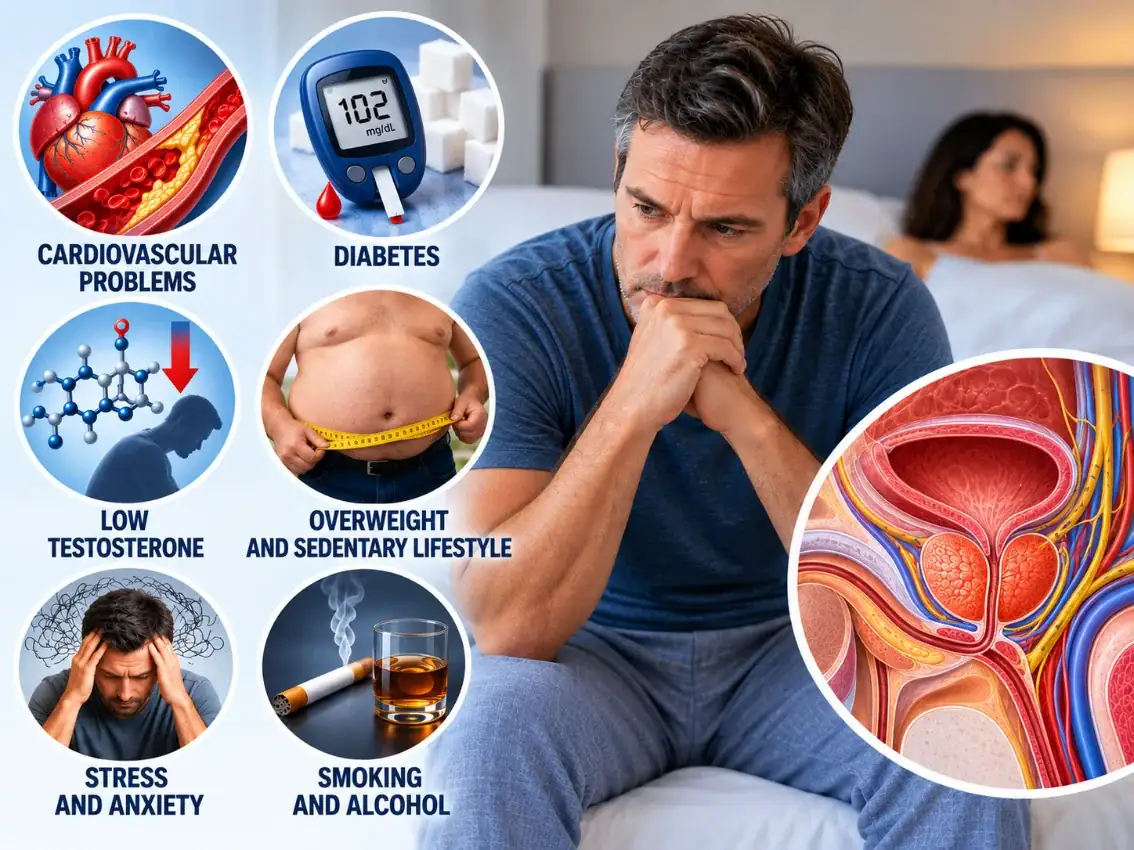
Erectile dysfunction after 40: discover vascular, hormonal and psychological causes, diagnostic tests, and evidence-based treatments. “After age 40, difficulty maintaining an erection may be the earliest warning sign of silent cardiovascular disease.”
Key Takeaways:
- Beyond Normal Aging: Erectile dysfunction after 40 is not an inevitable consequence of aging, but a clear sign of identifiable metabolic, hormonal, or vascular factors.
- Cardiovascular Warning Sign: Because penile arteries are narrow (1–2 mm), atherosclerosis often manifests as erectile difficulty years before coronary artery disease (Princeton IV Consensus).
- Integrated Systemic Factors: Hypertension, diabetes mellitus, low free testosterone, metabolic syndrome, obstructive sleep apnea, and chronic stress directly impair endothelial function.
- Specialized Diagnostic Workup: Penile dynamic duplex ultrasound and comprehensive endocrine blood panels accurately differentiate organic vascular disease from functional conditions.
- Evidence-Based Therapy: Modern management extends beyond symptomatic PDE5 inhibitors (Viagra, Cialis), focusing on microvascular restoration and addressing root etiologies.
Table of Contents
- 1. What is Erectile Dysfunction?
- 2. Why Does Erectile Dysfunction Increase After 40?
- 3. Cardiovascular Diseases: A Frequently Underestimated Cause
- Can Erectile Dysfunction Precede a Heart Attack?
- 4. Arterial Hypertension: Beyond Blood Pressure Numbers
- 5. Diabetes Mellitus: The Silent Enemy of Erectile Function
- 6. Low Testosterone: Is It Always to Blame?
- 7. Stress, Anxiety, and Performance Anxiety: The Cerebral Role
- 8. Sleep Deprivation and Obstructive Sleep Apnea (OSA)
- 9. Smoking, Alcohol, Obesity, and Sedentary Lifestyle
- 10. Medications That May Compromise Erection
- 11. Prostate Conditions, Pelvic Surgery, and Peyronie’s Disease
- 12. What Diagnostic Exams Are Indicated After Age 40?
- 13. How is Erectile Dysfunction Treated After 40?
- 14. Can Erectile Dysfunction Be Prevented?
- 15. Frequently Asked Questions About Erectile Dysfunction After 40
- Is it normal to have fewer erections after age 40?
- If I still have morning erections, does it prove my problem is purely psychological?
- Can erectile dysfunction be the earliest symptom of diabetes?
- Does Viagra permanently cure erectile dysfunction?
- When should I consult an urologist?
- Conclusion
- Essential Scientific References
Erectile dysfunction after 40 is a common disorder, yet it should never be considered an inevitable consequence of aging. Underlying difficulties in achieving or sustaining an erection often involve circulatory impairment, hormonal imbalances, diabetes, hypertension, stress, medication side effects, and lifestyle habits. In many individuals, erectile dysfunction represents one of the very first clinical indicators of undiagnosed cardiovascular disease.
Understanding the true underlying causes of erectile dysfunction not only restores sexual health and quality of life, but also enables the early detection of systemic conditions that could otherwise compromise overall longevity.
1. What is Erectile Dysfunction?

Erectile dysfunction (ED), historically termed sexual impotence, is defined as the persistent or recurrent inability to achieve or maintain a penile erection sufficient for satisfactory sexual performance.
It is crucial to distinguish occasional episodes from chronic dysfunction. Almost every man may experience isolated difficulties following extreme fatigue, severe psychological stress, excessive alcohol intake, or sleep deprivation.
An isolated episode does not constitute chronic erectile dysfunction. Medical evaluation is warranted when difficulties persist, recur systematically, or generate substantial personal and relationship distress.
Penile erection is a sophisticated neurovascular process requiring the synchronized harmony of multiple systems:
- Nervous system: transmits sexual stimuli from the central and autonomic pathways.
- Vascular system: delivers arterial inflow to engorge the corpora cavernosa.
- Endocrine system: modulates libido, nitric oxide pathways, and tissue responsiveness via testosterone.
- Cavernous smooth muscle: relaxes to allow arterial engorgement and compresses venules against the tunica albuginea to sustain rigidity.
- Psychological factors: modulate arousal, emotions, and interpersonal dynamics.
Disruption of any single component among these complex pathways is sufficient to impair erectile quality.
2. Why Does Erectile Dysfunction Increase After 40?
Advancing chronological age correlates with higher epidemiological incidence of vascular alterations, subclinical atherosclerosis, endothelial dysfunction, elevated fasting glucose, and chronic arterial hypertension.
These vascular modifications are frequently compounded by gradual reductions in bioavailable free testosterone, cumulative psychological stress, and years of sedentary habits.
However, a fundamental medical distinction must be emphasized: chronological age alone is not the direct cause of erectile dysfunction.
Many men maintain robust erectile function well into their 70s and 80s when microvascular health is preserved. When erectile difficulty arises in one’s 40s or 50s, it is almost invariably the manifestation of specific pathophysiological factors that require timely clinical identification.
3. Cardiovascular Diseases: A Frequently Underestimated Cause
One of the most clinically critical causes of erectile dysfunction is arterial atherosclerosis. Erection fundamentally relies on a massive, rapid surge of arterial blood flow into the cavernous bodies.
If the internal pudendal and cavernous arteries lose elasticity or develop atherosclerotic plaque narrowing, blood inflow becomes insufficient to generate or sustain adequate intracavernous pressure.
Can Erectile Dysfunction Precede a Heart Attack?
Yes. In men with vascular etiology, erectile dysfunction frequently precedes coronary events and symptomatic cardiovascular disease by 2 to 5 years.
This phenomenon is explained by the widely validated ‘artery size hypothesis’. Penile cavernous arteries measure approximately 1 to 2 mm in diameter, compared to 3 to 4 mm for coronary arteries and 5 to 7 mm for carotid arteries.
Consequently, identical systemic atherosclerotic plaques and endothelial damage manifest clinically in the smaller penile vessels long before producing angina pectoris or myocardial ischemia.
Therefore, new-onset erectile dysfunction in a man over 40 must never be dismissed as trivial stress; it serves as a crucial sentinel marker warranting thorough cardiovascular assessment.
4. Arterial Hypertension: Beyond Blood Pressure Numbers
Chronic arterial hypertension induces mechanical shear stress that damages the vascular endothelium—the delicate cellular monolayer lining all blood vessels.
Healthy endothelial cells synthesize nitric oxide (NO), the primary biochemical messenger responsible for smooth muscle relaxation and cavernous vasodilation. Hypertensive damage impairs nitric oxide bioavailability, preventing normal erection.
Furthermore, certain classical antihypertensive drug classes (notably non-selective beta-blockers and thiazide diuretics) can exacerbate erectile difficulties.
Patients should never self-discontinue antihypertensive medications. Instead, specialist consultation allows switching to erectile-neutral or vasodilating agents (such as ARBs, ACE inhibitors, or nebivolol).
5. Diabetes Mellitus: The Silent Enemy of Erectile Function

Diabetes mellitus is one of the most formidable risk factors for erectile dysfunction, which often occurs 10 to 15 years earlier in diabetic men compared to the non-diabetic population.
Chronic hyperglycemia damages both the microvasculature (diabetic microangiopathy) and the autonomic nerve fibers (diabetic autonomic neuropathy) responsible for transmitting erectile stimuli.
Diabetes also promotes advanced glycation end-products (AGEs), cavernous fibrosis, and concurrent metabolic syndrome with visceral adiposity.
In routine urological practice, an unexpected deterioration of erectile quality in a 40-year-old man is frequently the initial clinical sign that leads to diagnosing previously undetected type 2 diabetes or insulin resistance.
6. Low Testosterone: Is It Always to Blame?
Many men intuitively attribute any decline in sexual vigor exclusively to declining hormones. While testosterone is essential for sexual desire, nocturnal erections, and maintaining cavernous smooth muscle tone, it is rarely the sole culprit in isolated ED.
Physiological total testosterone declines gradually by approximately 1% per year after age 30, but clinical hypogonadism involves symptomatic deficiency.
Hypogonadism is suspected when erectile dysfunction coexists with marked loss of spontaneous libido, chronic fatigue, depressive mood, loss of lean muscle mass, and visceral fat accumulation.
Accurate diagnosis requires measuring early-morning total and free testosterone, SHBG, and LH. Testosterone replacement therapy must only be prescribed when clinical deficiency is biochemically confirmed, as blind supplementation carries risks and fails to correct primary vascular disease.
7. Stress, Anxiety, and Performance Anxiety: The Cerebral Role
Erection originates in the central nervous system. The brain acts as the primary sexual organ, balancing excitatory neurochemistry (dopamine, oxytocin) and inhibitory tone (adrenaline, noradrenaline).
Chronic professional stress, emotional exhaustion, and depressive states maintain a state of hyper-sympathetic activation. High circulating catecholamines cause vascular vasoconstriction, directly opposing penile arterial filling.
Performance anxiety frequently triggers a vicious cycle: an initial sporadic failure engenders anticipatory fear in subsequent encounters, where the patient shifts from participant to critical observer (‘spectatoring’), releasing adrenaline that instantly aborts erection.
A decisive clinical clue: the persistence of firm spontaneous morning or nocturnal erections strongly points toward a predominant psychogenic component, whereas the loss of both nocturnal and waking erections indicates organic vascular or hormonal pathology.
8. Sleep Deprivation and Obstructive Sleep Apnea (OSA)
Nocturnal erections occur during REM sleep cycles and are physiological exercises that oxygenate cavernous tissue, preserving its elastic structural properties.
Severe sleep fragmentation disrupts these restorative nocturnal cycles, suppresses the circadian peak of morning testosterone synthesis, and elevates cortisol.
Obstructive sleep apnea (OSA)—characterized by loud snoring, nocturnal gasping, and daytime somnolence—induces intermittent nocturnal hypoxia and systemic endothelial oxidative stress, dramatically elevating erectile dysfunction rates. Treating OSA with CPAP frequently yields noticeable improvements in erectile firmness.
9. Smoking, Alcohol, Obesity, and Sedentary Lifestyle
Cigarette smoking is an aggressive vascular toxin. Nicotine induces acute arterial vasoconstriction, while toxic combustion products accelerate cavernous atherosclerosis and destroy endothelial nitric oxide synthase.
Visceral obesity acts as an endocrine-active tissue: excess adipose mass produces inflammatory cytokines and aromatase enzymes that convert circulating testosterone into estrogens.
Regular aerobic physical activity (150–300 minutes per week) improves vascular elasticity, elevates bioavailable nitric oxide, and represents one of the most powerful, evidence-backed lifestyle interventions for preserving erectile function.
10. Medications That May Compromise Erection
Numerous widely prescribed pharmaceuticals can interfere with neurovascular erectile mechanisms:
- Antihypertensives: particularly older-generation beta-blockers and thiazide diuretics.
- Psychotropics: SSRIs and SNRIs antidepressants, tricyclics, and anxiolytics, which frequently impair libido, erection, and ejaculatory latency.
- Prostatic medications: 5-alpha reductase inhibitors (finasteride, dutasteride) may diminish libido and volume in susceptible patients.
- Gastrointestinal drugs: histamine H2-receptor antagonists in prolonged high doses.
Any adjustment or substitution of ongoing medical therapy must be executed collaboratively with your physician; never discontinue vital therapies independently.
11. Prostate Conditions, Pelvic Surgery, and Peyronie’s Disease
Chronic prostatitis and chronic pelvic pain syndrome (CPPS) frequently produce erectile discomfort, painful ejaculation, and autonomic pelvic floor hypertonia that disrupts erection.
Radical pelvic surgical procedures (such as radical prostatectomy (for an in-depth review of glandular function, see our guide to prostate anatomy and physiology) or colorectal resection) can injure the fragile neurovascular cavernous bundles running along the prostatic capsule.
Peyronie’s disease (induratio penis plastica), marked by acquired fibrous inelastic plaques in the tunica albuginea, causes penile curvature, localized pain, and venous leak dysfunction. Early urological evaluation is essential to halt progressive deformity.
12. What Diagnostic Exams Are Indicated After Age 40?
A meticulous diagnostic protocol moves through structured stages to uncover root causes:
| Examination / Test | Why It May Be Useful |
|---|---|
| Blood Glucose and HbA1c | Screen for diabetes and glycemic disorders |
| Lipid Profile (Cholesterol & Triglycerides) | Assess overall cardiovascular risk |
| Free Testosterone | Identify potential androgen deficiency |
| LH, FSH, Prolactin | Investigate specific neuro-endocrine dysfunctions |
| Blood Pressure & Waist Circumference | Evaluate cardiometabolic risk factors |
| Dynamic Penile Color Duplex Ultrasound | Examine the vascular inflow and cavernous dynamics in selected cases |
- Clinical history and validated questionnaires: quantifying severity via the International Index of Erectile Function (IIEF-5).
- Endocrine and metabolic blood panels: fasting blood glucose, HbA1c, lipid profile, total and free testosterone, SHBG, prolactin, TSH.
- Cardiovascular screening: resting blood pressure, ECG, and cardiological evaluation where occult ischemia is suspected.
- Penile Dynamic Color Duplex Ultrasound: the gold-standard functional investigation, assessing cavernous peak systolic velocity (arterial inflow) and resistive index (veno-occlusive competence) following pharmacological stimulation with prostaglandin E1.
13. How is Erectile Dysfunction Treated After 40?
Modern sexual medicine offers tailored, multi-tiered therapeutic modalities:
- Lifestyle optimization and risk factor management: smoking cessation, weight loss, glycemic control, and structured aerobic training.
- Oral PDE5 inhibitors: sildenafil, tadalafil, vardenafil, and avanafil. These facilitate smooth muscle relaxation when sexual stimulation is present, offered in on-demand or daily low-dose regimens.
- Hormonal replacement: targeted testosterone therapy when hypogonadism is clinically and biochemically documented.
- Regenerative low-intensity shockwave therapy (Li-ESWT): stimulating penile neoangiogenesis and endothelial regeneration in vasculogenic ED.
- Intracavernous pharmacotherapy or vacuum erection devices: for severe cases unresponsive to oral medications.
- Penile prosthesis implantation: the definitive surgical solution with highest patient-partner satisfaction rates for refractory end-stage organic impotence.
14. Can Erectile Dysfunction Be Prevented?
In the vast majority of men, vascular erectile dysfunction is largely preventable. Because penile microvessels share identical risk factors with coronary and carotid arteries, protecting vascular endothelium protects erectile capacity.
Prioritizing Mediterranean dietary patterns, regular aerobic exercise, smoking avoidance, maintaining healthy blood pressure, managing sleep apnea, and scheduling routine annual urological checkups after 40 represent the most effective long-term preventative strategy.
15. Frequently Asked Questions About Erectile Dysfunction After 40
Is it normal to have fewer erections after age 40?
While refractory periods may lengthen and arousal may require more direct tactile stimulation, chronic inability to achieve adequate rigidity is never ‘normal’ aging. It reflects identifiable vascular, hormonal, or neural issues.
If I still have morning erections, does it prove my problem is purely psychological?
Not entirely. While morning erections indicate that basic vascular and neural pathways are intact, early-stage vascular disease, endothelial fatigue, or situational performance anxiety can still coexist.
Can erectile dysfunction be the earliest symptom of diabetes?
Yes. In numerous men over 40, progressive erectile difficulty is the presenting clinical complaint that leads to the initial diagnosis of type 2 diabetes or metabolic syndrome.
Does Viagra permanently cure erectile dysfunction?
PDE5 inhibitors provide symptomatic support by augmenting blood flow during sexual arousal; however, they do not resolve underlying atherosclerosis, nerve injury, or hypogonadism. Comprehensive treatment must target the underlying etiology.
When should I consult an urologist?
Specialist evaluation is recommended whenever erectile difficulties persist for more than 3 months, occur recurrently, cause relationship distress, or coincide with known cardiovascular risk factors.
Conclusion
Erectile dysfunction after age 40 is far more than a localized sexual complaint. It should never be passively dismissed as stress or inevitable senescence.
In many individuals, the penile microvasculature serves as an invaluable early warning system for the entire arterial tree. The Princeton IV Consensus guidelines unequivocally affirm the sentinel role of vasculogenic ED in predicting broader cardiovascular risk.
Consulting an urological specialist ensures not only the restoration of a fulfilling sexual life, but also safeguards overall cardiovascular longevity through timely diagnosis and individualized care.
Essential Scientific References
- European Association of Urology. EAU Guidelines on Sexual and Reproductive Health. 2026 Edition. EAU Guidelines.
- Kloner RA, Burnett AL, Miner M, et al. Princeton IV consensus guidelines: PDE5 inhibitors and cardiac health. Journal of Sexual Medicine. 2024;21:90–116. DOI: 10.1093/jsxmed/qdae003. DOI: 10.1093/jsxmed/qdad165.
- Köhler TS, Kloner RA, Rosen RC, et al. The Princeton IV Consensus Recommendations for the Management of Erectile Dysfunction and Cardiovascular Disease. Mayo Clinic Proceedings. 2024;99:1500–1517. DOI: 10.1016/j.mayocp.2024.04.015. DOI: 10.1016/j.mayocp.2024.06.012.
Article by Prof. Federico Guercini, MD
Specialist in Urology and Andrology in Rome, internationally recognized for advanced clinical care and research in urological, prostatic, and male sexual health conditions.
To schedule a clinical consultation in Rome: Contact Prof. Guercini’s Clinic
